
Introduction
In December 2019, a novel severe respiratory syndrome coronavirus 2 (SARS-CoV-2) caused by Coronavirus 2019 (COVID-19) broke out in Wuhan, China. On March 11, 2020, the World Health Organisation declared COVID-19 a pandemic. Further, as of March 15, 2020, the WHO reported that more than 100 countries had been affected by the COVID-19 pandemic, with about 153,517 confirmed cases and 5735 deaths (https://www.who.int/#). Previous studies have recognised some clinical characteristics of COVID-19 including the median incubation period estimated to be 4 days (interquartile range, two to seven) [1], and the most common symptoms are fever, cough, shortness of breath, muscle pain, headache, chest pain, nausea, vomiting, and diarrhoea in some patients. Chest computed tomography (CT) mainly manifests as large patches in both lungs and ground-glass opacity. The disease rapidly progresses to acute respiratory distress syndrome (ARDS) and multiple organ failure, which results in death [2]. However, during the treatment process, we discovered some new challenges that need to be addressed.
Material and methods
Study design and participants
This is a single-centred, retrospective study. A total of 37 COVID-19 samples were collected from confirmed patients admitted from January 23 to February 25, 2020, at our hospital, Dazhou Central Hospital, Sichuan Province, China. The hospital admitted a total of 37 COVID-19 patients diagnosed by RT-PCR from the city. The study was approved by the Ethics Committee of Dazhou Central Hospital, and written informed consent was obtained from the patients.
Procedures
Patient demographics, clinical, laboratory, and other data were collected from the patients’ medical records. Their clinical results were followed up until March 18, 2020. All COVID-19 cases were detected from throat swabs, blood, and stool. During hospitalisation, the patients were tested for influenza A virus (H1N1, H3N2), influenza B virus, respiratory syncytial virus, adenovirus, and new coronavirus pneumonia, which are routinely screened in our laboratory. Real-time RT-PCR was used to detect viral nucleic acids from the throat swabs and stool. Also, all the patients underwent a chest CT scan.
Results
The study included 37 patients diagnosed with COVID-19, out of which 13 (35.1%) patients had a clear history of exposure to Wuhan, and the remaining 24 patients were imported second-generation cases. The average age of the patients was 45.76 ±13.1 years, and the maximum age was 82 years. The gender representation of the patients was 56.8% male and 43.2% female. The average duration of pharyngeal swabs was 20.65 ±6.7 days. Four (10.8%) patients were asymptomatic, all females, and the duration of nucleic acid positive in asymptomatic infections was 11–35 days (Table I).
Table I
Demographic characteristics of 37 patients with COVID-19
Elevated admission lactate was reported in 33 (89.1%) patients, 17 (45.9%) patients had elevated fibrinogen C (Fib-C), and 5 (13.5%) had elevated D-dimers. Based on the new coronavirus-specific antibodies (using the colloidal gold method, Guangzhou Wanfu Biotechnology Co., Ltd., production license number: 20030645), a total of 33 (4 patients did not undergo this test) cases were tested, out of which 29 (87.9%) tested positive and 4 (10.8%) were positive for stool nucleic acid (Table II).
Table II
Laboratory abnormalities reported among 37 patients with confirmed COVID-19
During hospitalisation, screening of all the patients for influenza A virus (H1N1, H3N2), influenza B virus, respiratory syncytial virus, and adenovirus antigen/antibody was performed. All the patients tested negative for all the above viruses but showed lung consolidation. Patients with significantly elevated infection parameters had a sputum culture, and patient sputum culture specimens were sent on the 10th day after onset; only 1 (2.7%) of the patients had developed Klebsiella pneumonia with no history of concomitant disease. However, the patient improved after antibiotic treatment.
Among all the COVID-19-confirmed patients, 35 (94.6%) patients were treated with α-interferon nebulisation combined with Abidol or lopinavir/ritonavir antiviral therapy. A total of 12 (32.4%) patients were treated with Abidol and 23 (62.2%) patients with lopinavir/ritonavir. Elevated infection parameters (leukocyte, C-reactive protein, or calcitonin source) or positive sputum culture were reported in 7 (18.9%) patients. For patients with lower lymphocytes and longer nucleic acid positive duration, human immunoglobulin 10 g/day was administered for 3–5 days. Only a few patients experienced a transient increase in transaminase and poor appetite during antiviral treatment. Because COVID-19 is a new infectious disease with rapid transmission, psychological intervention is also necessary for some patients who may develop anxiety and depression. A total of 4 (10.8%) patients received psychological intervention (Table III). Previous studies by Cao et al. have found that lopinavir/ritonavir does not provide good therapeutic benefit in the treatment of patients with severe COVID-19 infection [3]. Our findings were similar to those of previous studies. By comparing the number of nucleic acid-positive days in patients treated with lopinavir/ritonavir, it was found that these drugs had no significant effect on the number of nucleic acid-positive days (Table IV). Previous studies also suggested that Abidol could effectively inhibit COVID-19 replication [4]. However, our study found that its effect on the time of nucleic acid positivity was not significant (Table V).
Table III
Co-infection of 37 COVID-19 patients during hospitalisation
| Co-infection | Patients |
|---|---|
| Other viruses | 0 |
| Bacteria | Klebsiella pneumonia (1/37, 2.7%) |
| Fungus | 0 |
Table IV
Treatment strategies for COVID-19 patients during hospitalisation
Table V
Statistics on the use of antiviral drugs in 37 patients with COVID-19
| Drugs | Patients | Nucleic acid positive days |
|---|---|---|
| Lopinavir/ritonavir | 23 | 22.29 ±7.42 |
| Unused lopinavir/ritonavir | 14 | 19.65 ±6.19 |
| P-value | > 0.05 | |
| Abidol | 12 | 22.42 ±7.57 |
| Unused abidol | 25 | 19.80 ±6.23 |
| P-value | > 0.05 |
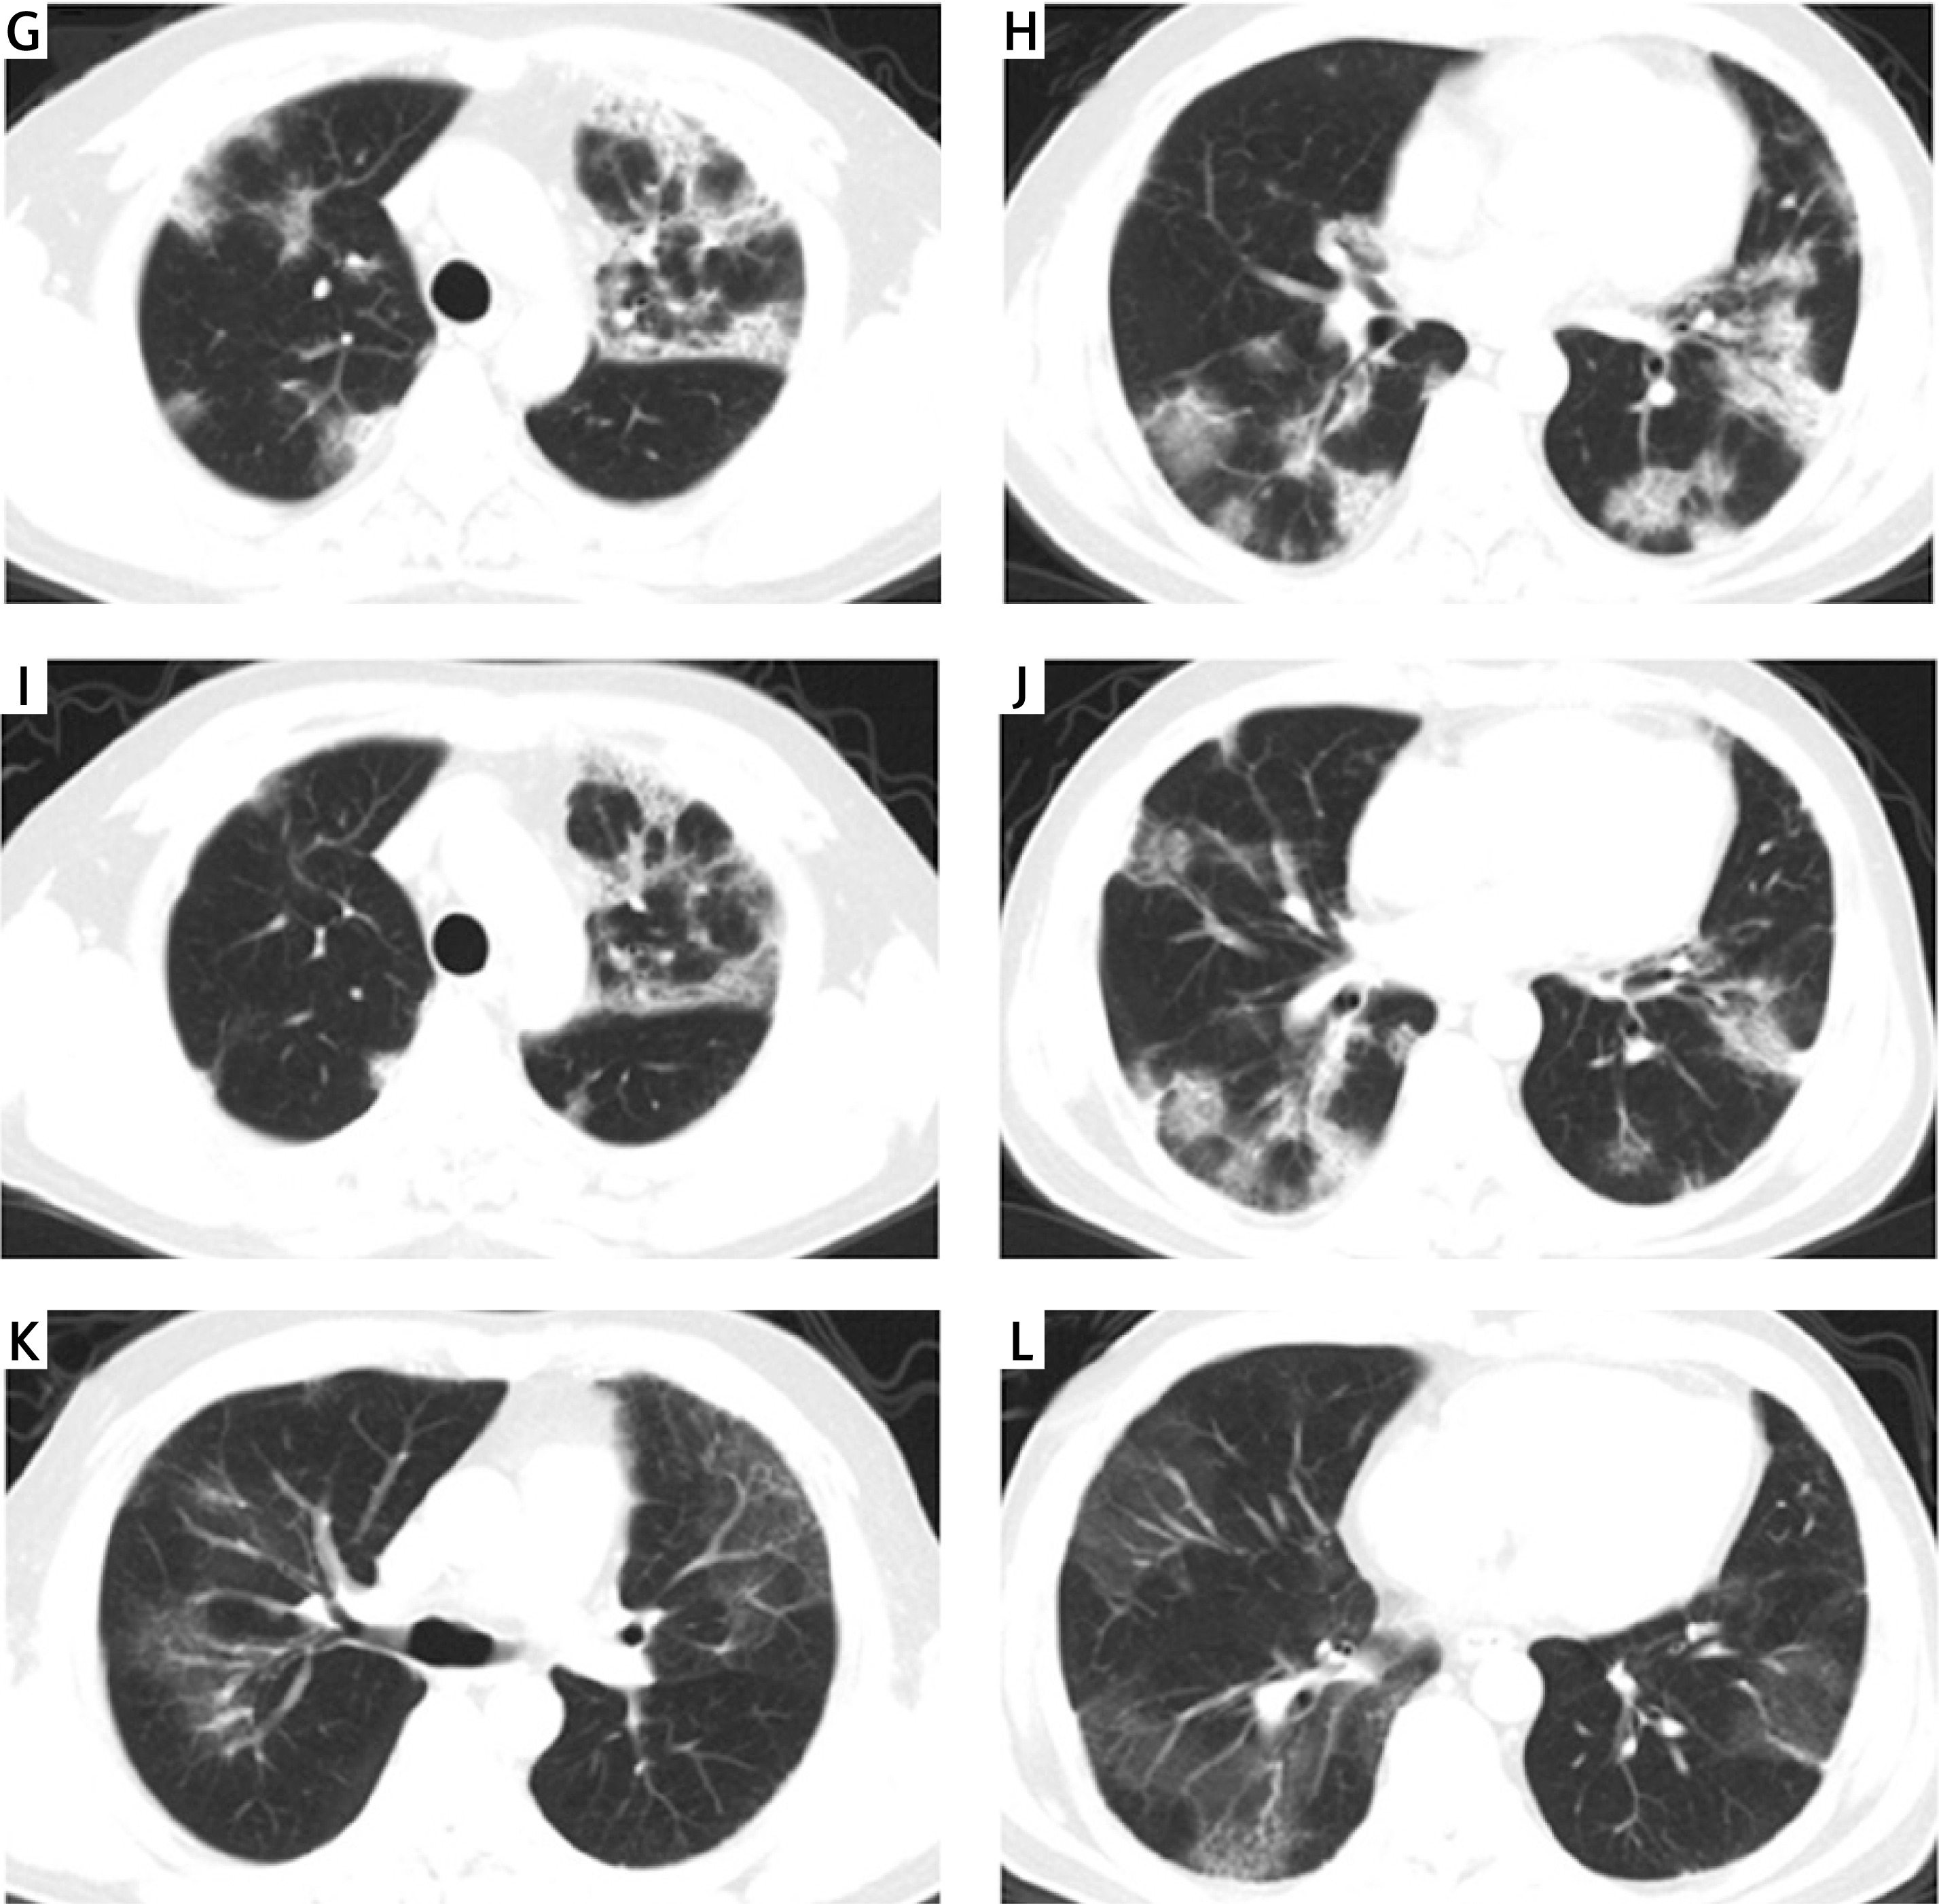
Typical imaging features from one of the patients with diabetes and SARS-CoV-2 were collected. At onset, the ground-glass opacity of both lungs progressed rapidly and gradually changed. This suggested an increase in exudation in both lungs, reaching a peak of exudation at about 15 days. The entire course of this patient’s covid-19 was 2 months (Figure 1).
Discussion
Coronavirus is an enveloped positive-sense RNA virus, belonging to the Coronaviridae and segment-free virus families [5]. SARS-CoV-2 is among the seven coronaviruses that can infect humans. The other six coronaviruses include HCoV-229E, HCoV-NL63, HCoV-OC43, HCoV-HKU1, SARS-CoV, and MERS-CoV3. SARS-CoV-2, SARS-CoV, and MERS-CoV3 are highly pathogenic and can cause severe human respiratory syndrome, and the other four causes mild upper respiratory disease [6–10]. The mortality of SARS-CoV-2 has been reported to be more than 10% and MERS-CoV at more than 35% [11, 12]. However, the SARS-CoV-2 mortality rate is currently estimated at 2–5% [13].
Previous studies have reported the clinical characteristics and treatment strategies for patients infected with SARS-CoV-2. SARS-CoV-2 can cause coagulopathy and even death [14]. Among COVID-19 patients, 5 (13.5%) had elevated D-dimer, and 17 (45.9%) had elevated Fib-C. The increase in Fib-C indicated possibilities of blood coagulation; therefore, there is a need to pay close attention to the risk of deep vein thrombosis [15, 16]. Elevated D-dimer is often used as an indicator of pulmonary embolism, but it can also be elevated in inflammatory diseases. Studies by Han et al. [17, 18] reported that patients with severe SARS-CoV-2 infection had higher D-dimer. In mild patients, monitoring of the D-dimer values may help in the early detection of severe cases. Gao et al. [19] proposed that D-dimer has important clinical value in early prediction of the severity of COVID-19.
The increase in lactic acid is often caused by anaerobic fermentation. We found that 33 (89.1%) patients had increased lactic acid, which was mainly accumulated in the lungs. We speculated that in the early stages of the disease, patients experience different levels of hypoxia due to lung infiltration or fever. Therefore, there is a need to correct the hypoxia in COVID-19 patients in good time. Peng et al. [20] also found that lactic acid accumulation and thrombosis can exacerbate the risk of death in COVID-19 patients. Therefore, we advocate for close monitoring of the patients’ lactic acid, internal environmental conditions, and hypoxia, to prevent the disease from aggravating to multiple organ failure and even death.
Generally, IgM can be produced 3–5 days after exposure to pathogenic microorganisms. IgG usually appears after IgM and can persist for many years after the infection. In this study, 33 patients confirmed to have COVID-19 were tested, and 29 (87.9%) were positive or weakly positive. However, Li et al. [21] tested for IgM and IgG antibodies in 25 COVID-19-confirmed patients, and they found 96% clinical sensitivity and 100% specificity of the tests. Therefore, detection using the new coronavirus IgM and IgG antibodies can help counteract the inadequacies presented by the nucleic acid detection methods.
Some new challenges currently being faced were identified in this study. For example, among the 37 COVID-19 patients, 4 (10.8%) had positive nucleic acid in their stool. Zhang et al. [22–24] also reported a small number of cases with positive nucleic acid in stool. One of the patients tested positive for viral nucleic acid in the stool for more than 40 days, and 2 patients experienced intermittent abdominal pain. Therefore, we recommend that the virus in the stool be isolated and cultured from the patient to further confirm the existence of faecal-oral transmission. This will help to provide additional effective measures for the public against the spread of COVID-19.
Psychological problems caused by COVID-19 in patients cannot be ignored. In this study, we found that 4 (10.8%) patients experienced severe anxiety and depression and needed psychological intervention to reduce the psychological trauma. At the same time, the patients’ infection parameters needed to be closely monitored. COVID-19, like other viral types of pneumonia, may present as a viral or bacterial infection at an early stage [25–27]. A total of 5 patients with positive pharyngeal swabs for more than 15 days and a decreased lymph count received intravenous immunoglobulin, and their lymphocyte count was reported to have improved significantly. Fu et al. [28] reported that the use of intravenous immunoglobulin can block FcR activation in the absence of a proven clinical FcR blocker to treat lung inflammation and prevent severe lung injury. Therefore, the intravenous immunoglobulin used in this study may have some effects in preventing disease progression. However, this requires further studies. In addition, previous studies suggested that regulation of renin-angiotensin system (RAS) and lipid might also be a new treatment for COVID-19 [29–31]. By comparing the number of cloudy days of throat swab nucleic acid in patients treated with lopinavir/ritonavir and Abidol, it was found lopinavir/ritonavir and Abidol may not be effective in treating COVID-19; however, the number of cases in this study was small, and further research using large sample data should be conducted to determine their effectiveness. In terms of susceptibility to COVID-19, Bianconi et al. found that particulate matter pollution significantly increased the probability of infection with COVID-19 [32]. This may also serve as a warning about the over-modification of nature by human beings. As research on COVID-19 continues to progress [33, 34], we will eventually find treatments for this entirely new virus.
In conclusion, in the serum of most COVID-19 infected patients, lactic acid was higher than normal, and COVID-19-specific antibody was positive. Fib-C and D-dimer in the serum of some infected patients increased. Particular attention should be paid to the changes in lactic acid, Fib-C, and D-dimer in patients with COVID-19 to prevent disease progression. The new coronavirus-specific IgM and IgG antibodies can be used to supplement the nucleic acid detection methods for COVID-19 because they provide rapid results. Lopinavir/ritonavir and Abidol have little effect on shortening the positive time of viral nucleic acid in patients.

