Current issue
Archive
Manuscripts accepted
About the Journal
Editorial office
Editorial board
Section Editors
Abstracting and indexing
Subscription
Contact
Ethical standards and procedures
Most read articles
Instructions for authors
Article Processing Charge (APC)
Regulations of paying article processing charge (APC)

Editor's Choice
CARDIOVASCULAR PREVENTION / RESEARCH LETTER
Clinical Outcomes Following GLP-1 Receptor Agonist Initiation With Versus Without Background SGLT2 Inhibitor Therapy in Heart Failure with Preserved Ejection Fraction and Type 2 Diabetes: A Propensity-Matched Real-World Analysis
1
Endeavor Health Cardiovascular Institute, Glenview, Illinois, United States, United States
2
Medical University of Lodz, Lodz, Poland, Poland
3
Maimonides Medical Center, 4802 10th Ave, Brooklyn, NY 11219, United States, United States
4
SUNY Upstate Medical University, Syracuse, NY, United States, United States
5
ESIC Medical College and PGIMSR, Chennai, Tamil Nadu, India, United States
6
Department of Preventive Cardiology and Lipidology, Medical University of Lodz, Lodz, Poland;
Department of Cardiology and Congenital Heart Diseases of Adults, Polish Mother’s Memorial Hospital Research Institute (PMMHRI), Lodz, Poland, Poland
Submission date: 2026-10-30
Acceptance date: 2026-10-31
Online publication date: 2026-11-06
Corresponding author
Agata Magdalena Bielecka-Dabrowa
Department of Preventive Cardiology and Lipidology, Medical University of Lodz, Lodz, Poland; Department of Cardiology and Congenital Heart Diseases of Adults, Polish Mother’s Memorial Hospital Research Institute (PMMHRI), Lodz, Poland, Poland
Department of Preventive Cardiology and Lipidology, Medical University of Lodz, Lodz, Poland; Department of Cardiology and Congenital Heart Diseases of Adults, Polish Mother’s Memorial Hospital Research Institute (PMMHRI), Lodz, Poland, Poland
KEYWORDS
TOPICS
ABSTRACT
Introduction:
SGLT2 inhibitors (SGLT2i) improve heart failure outcomes, and GLP-1 receptor agonists (GLP-1 RA) confer cardiometabolic benefit. However, outcomes after GLP-1 RA initiation according to background SGLT2i use remain uncertain.
Material and Methods:
Using TriNetX, we compared GLP-1 RA initiation in patients with HFpEF and type 2 diabetes with versus without background SGLT2i. Cohorts were propensity-matched 1:1 and followed for one year, with 60-day landmark analyses.
Results:
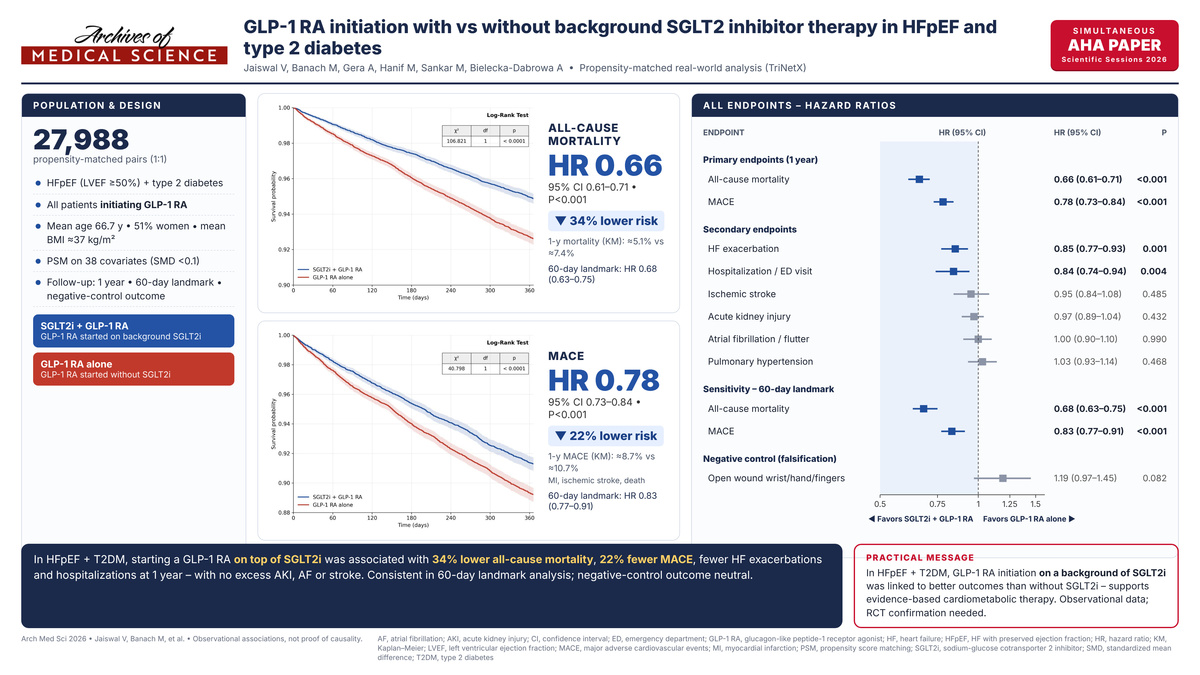
Among 27,988 matched pairs, background SGLT2i was associated with lower one-year all-cause mortality (HR 0.66, 95% CI 0.61–0.71) and major adverse cardiovascular events (MACE; HR 0.78, 95% CI 0.73–0.84; both P < 0.001). Landmark analyses were consistent for ACM (HR 0.68, 95% CI 0.63–0.75) and MACE (HR 0.83, 95% CI 0.77–0.91).
Conclusions:
In HFpEF with type 2 diabetes, GLP-1 RA initiation on a background of SGLT2i therapy was associated with lower mortality and MACE than initiation without SGLT2i.
SGLT2 inhibitors (SGLT2i) improve heart failure outcomes, and GLP-1 receptor agonists (GLP-1 RA) confer cardiometabolic benefit. However, outcomes after GLP-1 RA initiation according to background SGLT2i use remain uncertain.
Material and Methods:
Using TriNetX, we compared GLP-1 RA initiation in patients with HFpEF and type 2 diabetes with versus without background SGLT2i. Cohorts were propensity-matched 1:1 and followed for one year, with 60-day landmark analyses.
Results:
Among 27,988 matched pairs, background SGLT2i was associated with lower one-year all-cause mortality (HR 0.66, 95% CI 0.61–0.71) and major adverse cardiovascular events (MACE; HR 0.78, 95% CI 0.73–0.84; both P < 0.001). Landmark analyses were consistent for ACM (HR 0.68, 95% CI 0.63–0.75) and MACE (HR 0.83, 95% CI 0.77–0.91).
Conclusions:
In HFpEF with type 2 diabetes, GLP-1 RA initiation on a background of SGLT2i therapy was associated with lower mortality and MACE than initiation without SGLT2i.
REFERENCES (13)
1.
Packer M, Lam CSP, Lund LH, et al. Characterization of the inflammatory-metabolic phenotype of heart failure with a preserved ejection fraction: a hypothesis to explain influence of obesity. Eur J Heart Fail. 2020;22:1997–2005.
2.
Borlaug BA. Evaluation and management of heart failure with preserved ejection fraction. Nat Rev Cardiol. 2020;17:559–573.
3.
Solomon SD, McMurray JJV, Claggett B, et al. Dapagliflozin in heart failure with mildly reduced or preserved ejection fraction. N Engl J Med. 2022;387:1089–1098.
4.
Anker SD, Butler J, Filippatos G, et al. Empagliflozin in heart failure with a preserved ejection fraction. N Engl J Med. 2021;385:1451–1461.
5.
Marso SP, Daniels GH, Brown-Frandsen K, et al. Liraglutide and cardiovascular outcomes in type 2 diabetes. N Engl J Med. 2016;375:311–322.
6.
Kosiborod MN, Abildstrøm SZ, Borlaug BA, et al. Semaglutide in patients with heart failure with preserved ejection fraction and obesity. N Engl J Med. 2023;389:1069–1084.
7.
Kosiborod MN, Petrie MC, Borlaug BA, et al. Semaglutide in patients with obesity-related heart failure and type 2 diabetes. N Engl J Med. 2024;390:1394–1407.
8.
Zelniker TA, Wiviott SD, Raz I, et al. SGLT2 inhibitors for primary and secondary prevention of cardiovascular and renal outcomes in type 2 diabetes: a systematic review and meta-analysis of cardiovascular outcome trials. Lancet. 2019;393:31–39.
9.
Køber L, Adamo M, et al. 2026 ESC Guidelines for the management of heart failure. European Heart Journal. 2026. doi:10.1093/eurheartj/ehag100.
10.
Marx N, Federici M, Schütt K, et al. 2023 ESC Guidelines for the management of cardiovascular disease in patients with diabetes. Eur Heart J. 2023;44:4043–4140. doi:10.1093/eurheartj/ehad192.
11.
Lipsitch M, Tchetgen Tchetgen E, Cohen T. Negative controls: a tool for detecting confounding and bias in observational studies. Epidemiology. 2010;21(3):383–388.
12.
TriNetX. Trusted Global Real-World Data for Research [Internet]. 2026. Available from: https://trinetx.com/.
13.
Sabouret PF, Bernardi M, Santos RD, Rosencher J, Cacciatore S, Dib JC, Asher E, Giamundo DM, Biondi-Zoccai G, Andò G, Banach M, Lellouche N, Spadafora L. GLP-1 receptor agonists and SGLT2 inhibitors in cardiovascular practice: insights from a national survey of French cardiologists. Arch Med Sci. 2026 Jul 26;22(4):2465-2468.
Share
RELATED ARTICLE
| eISSN: | 1896-9151 |
| ISSN: | 1734-1922 |

We process personal data collected when visiting the website. The function of obtaining information about users and their behavior is carried out by voluntarily entered information in forms and saving cookies in end devices. Data, including cookies, are used to provide services, improve the user experience and to analyze the traffic in accordance with the Privacy policy. Data are also collected and processed by Google Analytics tool (more).
You can change cookies settings in your browser. Restricted use of cookies in the browser configuration may affect some functionalities of the website.
You can change cookies settings in your browser. Restricted use of cookies in the browser configuration may affect some functionalities of the website.
